
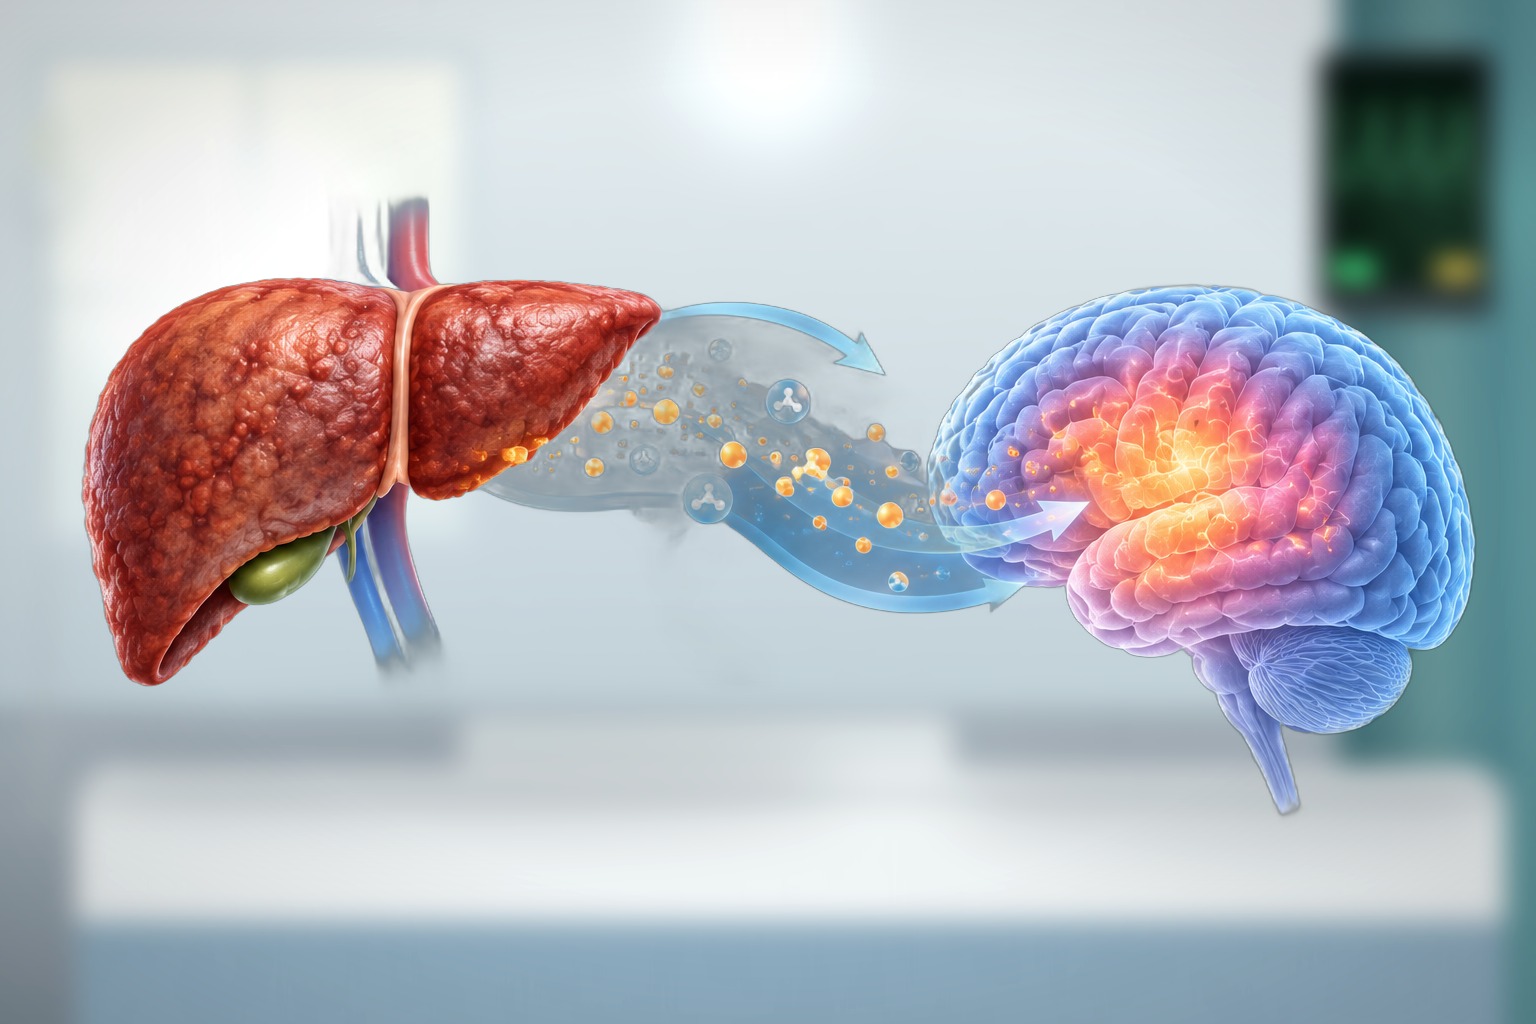
If you are reading this, you or someone close to you probably already lives with advanced liver cirrhosis and has had at least one episode of hepatic encephalopathy. It is a frightening moment: a person's speech, focus or awareness changes, often with little warning. At this stage, most families are no longer asking "What is hepatic encephalopathy?" They are asking more urgent questions. Why is this happening now? How do we stop it from happening again? When should we rush to the hospital? And does this mean the liver now needs a transplant?
This guide is written for exactly this stage. It does not explain cirrhosis from the beginning. Instead, it answers the practical questions you face right now as a patient or caregiver, including how repeated episodes relate to a liver transplant assessment.
1. What Is Hepatic Coma, and How Is It Related to Hepatic Encephalopathy?
Hepatic coma is the most severe stage of hepatic encephalopathy (West Haven Grade IV). The patient is completely unconscious and does not respond to what is happening around them. Many families hear both terms and wonder whether they are different conditions. The answer is simple: every hepatic coma is hepatic encephalopathy at its most severe, but not everyone with hepatic encephalopathy reaches this stage.
1.1 How long does a hepatic coma last?
There is no single answer for every case. If the trigger (for example an infection, bleeding or dehydration) is found and treated quickly, some patients regain consciousness within a few days. In more severe cases, especially when other organs are also affected, monitoring in the intensive care unit (ICU) may take longer, and no fixed duration can be predicted in advance. This is exactly why the patient needs continuous medical monitoring throughout this period.
1.2 Can hepatic coma be treated at home?
No, never. Hepatic coma is an emergency that requires immediate hospital admission, usually to the ICU. There the patient receives continuous monitoring, intravenous (IV) treatment and, sometimes, breathing support. There is no safe way to manage loss of consciousness caused by hepatic encephalopathy at home, even if the patient seems stable at first.
1.3 Can liver cancer cause hepatic coma?
Yes, in some cases. When liver cancer (most commonly hepatocellular carcinoma, HCC) seriously reduces the function of the remaining healthy liver tissue, either because of the tumor's size or because of the cirrhosis that often comes with it, toxins can build up in the blood. This can lead to hepatic encephalopathy and, in severe cases, coma, through the same process seen in advanced cirrhosis from other causes. The exact cause in each case is determined by the treating medical team, and treatment depends on it.
2. What Hepatic Encephalopathy Means at This Stage of Liver Disease?
When cirrhosis progresses to the decompensated stage, the liver loses much of its ability to filter out toxins that the body produces naturally. The most important of these is ammonia, which is produced when protein is digested in the gut. These toxins build up in the blood and reach the brain, where they affect concentration, memory, behavior and level of consciousness. This is hepatic encephalopathy.
The key point for your family at this stage: a single clear episode of hepatic encephalopathy (known as overt HE, meaning more than just mild slowing of thought) is medically considered a sign that cirrhosis has become decompensated. This is the same stage in which other complications may appear, such as ascites (fluid build-up in the abdomen) or bleeding from esophageal varices (enlarged veins in the esophagus). It does not necessarily mean everything has suddenly got worse, but it is a signal that calls for closer and more regular medical follow-up than before.
3. Symptoms of Hepatic Encephalopathy: From Mild to Severe
Symptoms can vary a lot from one episode to the next. Doctors grade them using the West Haven criteria, which help the medical team judge how serious an episode is and choose the right treatment plan.
It is important for families to know that these symptoms are often reversible when the trigger and the episode itself are treated quickly. This is why recognizing them early and acting fast matters so much.
4. When Does It Become a Medical Emergency?
This is the most important section of this article. Please read it carefully and share it with everyone involved in the patient's care. Go to the emergency department (ER) immediately if any of the following signs appear:
Never try to manage these situations at home or wait for the patient to "get better on their own". Loss of consciousness or severe confusion caused by hepatic encephalopathy can get worse quickly. It needs assessment and monitoring in a properly equipped medical setting, and it may require breathing support or urgent IV treatment. Even if the patient's last episode was mild and they recovered at home, any new episode that is more severe or different deserves immediate medical assessment. Do not judge it by comparing it with what happened before.
5. What Usually Triggers Episodes of Hepatic Encephalopathy?
Here is some news that reassures many families: most episodes have a clear trigger that can be identified and treated. They are not random, unexplained declines. The most common triggers include:
In practice, knowing this list means the best prevention is often not another medicine but simple daily attention: tracking bowel movements, watching for early signs of infection, and taking medicines strictly on time.
6. How Is an Acute Episode of Hepatic Encephalopathy Treated?
When an episode happens, the medical team usually follows two parallel tracks:
Mild to moderate episodes can sometimes be controlled with close monitoring and an adjusted lactulose dose. Severe episodes, especially with profound confusion or loss of consciousness, require hospital admission for continuous monitoring, IV treatment and management of any other complications.
7. Lactulose and Rifaximin: How They Differ and Why They Are Sometimes Used Together?
These two medicines are the foundation of treating hepatic encephalopathy and preventing it from coming back, but they work in different ways.
Lactulose is usually the first-line treatment. It speeds up bowel movements and changes the environment inside the gut so that less ammonia is absorbed into the blood. The dose is adjusted for each patient, with the aim of 2 to 3 soft bowel movements per day. This is the practical measure doctors use to judge whether the dose is right; there is no single fixed dose for everyone. Too little will not control ammonia. Too much can cause severe diarrhea and dehydration, which can trigger a new episode.
Rifaximin is an antibiotic that acts locally in the gut (very little is absorbed into the bloodstream). It reduces the number of ammonia-producing bacteria in the colon. It is not usually used instead of lactulose. It is added to lactulose, most often after a second episode of overt hepatic encephalopathy (secondary prevention), or when lactulose alone is not enough to control episodes despite being taken correctly.
The practical message for every patient and family: missing doses of these two medicines is one of the most common, and most avoidable, reasons that episodes come back. If lactulose is hard to tolerate (for example, because of troublesome diarrhea), discuss it with the doctor so the dose can be adjusted. Do not stop it on your own.
8. How Can Repeat Episodes Be Prevented?
After a first episode, the main goal is to reduce the chance of another one. The most useful practical steps are:
9. What Do Repeated or Worsening Episodes Mean for the Course of Liver Disease?
A single episode that was quickly controlled after treating a clear trigger (such as a minor infection) does not necessarily mean a major decline in the liver's own function. However, episodes that keep coming back despite good treatment, that become more severe over time, or that are hard to control with the usual medicines are an important medical sign. They suggest that liver function is declining further and that the liver is approaching liver failure, a stage at which medicines alone can no longer manage complications in the long term.
This is exactly why recurrent or hard-to-control hepatic encephalopathy is one of the most important signals that leads doctors to discuss a liver transplant assessment with the patient and family. The next section covers this in detail.
10. Hepatic Encephalopathy and Liver Transplantation
This point needs careful explanation. Many patients hear the words "liver transplant" after their very first episode and worry unnecessarily, while others delay the conversation even though they really do need an assessment.
The accurate medical picture:
10.1 When should you discuss a liver transplant assessment with a specialist?
If you or a family member has had two or more episodes of overt hepatic encephalopathy within a relatively short period, or if episodes are becoming harder to control despite taking lactulose and rifaximin correctly, this is the right time to ask for an assessment by a liver transplant team. There is no need to wait until the situation becomes critical.
10.2 What does the medical team examine during a liver transplant assessment?
The assessment usually covers: overall liver function (blood tests and scores such as MELD and Child-Pugh), the number and severity of hepatic encephalopathy episodes and any other complications of cirrhosis, the patient's general health and ability to tolerate major surgery, and whether there are any medical contraindications to transplantation. The decision is made by a multidisciplinary team after reviewing the full file and test results, not by any single measure.
10.3 Why is a liver transplant different from treating hepatic encephalopathy episodes?
Lactulose and rifaximin treat the result of poor liver function (the build-up of toxins). They do not treat the cause, which is the damaged liver itself. When a transplant is suitable, it replaces the liver that can no longer do its job with a healthy one that can filter toxins normally. This treats the problem at its root instead of continuing to manage its symptoms. This does not mean a transplant is right for every patient, but it explains why it becomes part of the medical discussion when episodes keep returning despite good treatment.
11. Practical Tips for Patients and Caregivers in Daily Life
Conclusion
Living with advanced cirrhosis and episodes of hepatic encephalopathy is exhausting, emotionally and physically, for you and for your family. It is natural to feel anxious with every new episode or every small change you notice. But knowing the emergency signs, following the treatment plan and watching for everyday triggers give you and your family real control over this stage.
If episodes keep returning despite good treatment, or if you want to find out whether a liver transplant might be the right step for you, the first step is simple. Send us your medical file and reports on previous episodes, and our medical team specialized in liver disease and transplantation in Turkey will review them. They will tell you clearly where your condition stands and what the most suitable next step is for you, before you decide to travel or make any decision.

Have a similar medical question?
Free medical file evaluation — Reply within 24 hours — Specialist team
Talk to our medical team+90 537 691 76 95 — Available 7 days a week




